Important Note Regarding Appointment Availability - Click Here

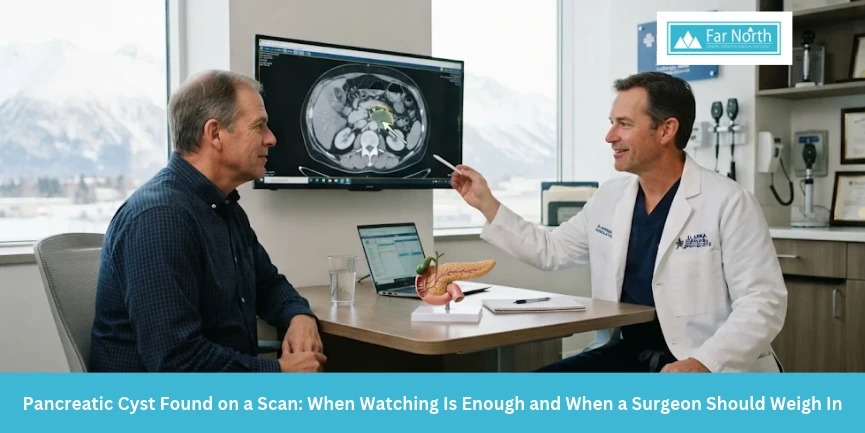
You went in for back pain or a kidney stone, and the scan report mentioned something else: a small cyst on the pancreas. The word alone can feel alarming, especially when nothing about how you feel has changed.
A pancreatic cyst is often a quiet finding, and many never cause harm. Others deserve careful tracking, and a few call for surgery. Knowing which category a cyst falls into starts with understanding its type, its size, and the features that doctors watch closely.
A pancreatic cyst is a fluid-filled sac in or on the pancreas, the gland behind the stomach that helps with digestion and blood sugar control. Most cause no symptoms and are discovered by chance during CT or MRI scans done for another reason.
When symptoms do appear, they may include upper abdominal pain, back pain, or a feeling of fullness, though these also have many other causes.
They are not all alike. Pseudocysts usually follow an episode of pancreatitis and are not precancerous. Serous cysts are generally benign. Mucinous types, including intraductal papillary mucinous neoplasms (IPMNs), can change over time, which is why they are followed.
These cysts are fairly common. One study of healthy people found that about 2.6 in 100 had an IPMN, and most never become cancer. Pancreatic cysts and tumors are among the conditions evaluated in gastrointestinal surgery.
Size alone does not decide a cyst's course. Specialists look at a group of features, and more than one raises the level of attention. Guidelines describe worrisome features such as:
Higher-risk findings include jaundice caused by the cyst, a solid nodule of 5 mm or more, or a main duct of 10 mm or more. Pancreatitis or new-onset diabetes also prompts faster evaluation.
Worrisome features do not mean cancer. They mean a cyst deserves a closer look, often with endoscopic ultrasound. High-risk features carry a stronger case for surgery, although guidelines differ on whether any single finding is enough.
Monitoring usually begins with MRI, which shows the cyst and its connection to the pancreatic duct clearly. CT is also used. When a cyst is larger or has worrisome features, endoscopic ultrasound allows a closer look and, when needed, sampling of cyst fluid.
Repeat imaging intervals vary by guideline, cyst size, and risk. Cysts without concerning features are often rechecked every 6 to 24 months, while concerning features usually shorten that timeline to around 6 months. Pseudocysts and serous cysts generally do not need ongoing surveillance.
Tests have limits. No scan can say with certainty whether a mucinous cyst will turn cancerous, so surveillance relies on patterns over time rather than a single image. Fluid analysis can add information, though it is reserved for cases where results would change the plan.
Guidelines also differ on how long to continue, from five years of stability to lifelong follow-up. Age and overall health matter too, so the plan should be individualized and revisited over time. Ask which guideline your plan follows and when the next scan is due.
Surgery is considered when a cyst shows high-risk features, and it is weighed carefully when worrisome features are present. The decision balances the chance of cancer against the risks of an operation, along with age and overall health.
The operation depends on where the cyst sits. Cysts in the body or tail are often removed with a distal pancreatectomy, sometimes using minimally invasive techniques. Cysts in the head of the pancreas are typically treated with a Whipple procedure, which falls under surgical oncology.
Not every cyst with worrisome features goes to the operating room. For an older patient or someone with other health conditions, careful surveillance may be safer than a major operation. A surgical opinion helps weigh these tradeoffs before a decision is made.
After removal, a pathologist examines the tissue for abnormal cell changes or cancer. Recovery depends on the procedure, so asking about the expected hospital stay, diet changes, and follow-up imaging in advance is reasonable. Reviewing what to expect before an operation also helps patients prepare.
A pancreatic cyst on a scan is not a diagnosis of cancer. Many are harmless, some need regular imaging, and a few call for surgery. What matters is identifying the type, measuring change over time, and recognizing the features that tip the balance.
A clear plan replaces uncertainty, and a surgical opinion can help when findings fall in a gray area. Asking questions early, while nothing is urgent, gives you time to choose a plan with confidence.
If a scan has left you with questions, Far North Surgery in Anchorage can review your findings and talk through options. Contact us to schedule a consultation.
No. Most pancreatic cysts are not cancer, and many never become cancer. Certain types, such as mucinous cysts, can change over time, which is why some are followed with repeat imaging. A specialist can explain which type applies to your scan.
No. Surgery is generally reserved for cysts with high-risk features, or worrisome features where the benefits outweigh the risks. Many cysts, including pseudocysts and serous cysts, need little or no ongoing treatment. A surgeon can help weigh the tradeoffs.
Jaundice (yellowing of the skin or eyes), persistent abdominal or back pain, unexplained weight loss, new diabetes, or an episode of pancreatitis deserve prompt medical attention. Severe pain or fever needs urgent care.
A gastroenterologist or a surgeon with pancreatic experience can review the images, order further testing such as endoscopic ultrasound, and coordinate follow-up. Bringing the scan report and images to the appointment helps.